Popular Lab Tests That Lack Sufficient Evidence for Routine Use
Many widely ordered lab tests lack evidence they actually help healthy people.

If a test is easy to buy, widely ordered, or bundled into a glossy wellness panel, that says nothing about whether it helps healthy people stay healthy. That's the gap this piece is built around: popularity and evidence are two different standards, and a lot of commercially successful lab tests only clear one of them.
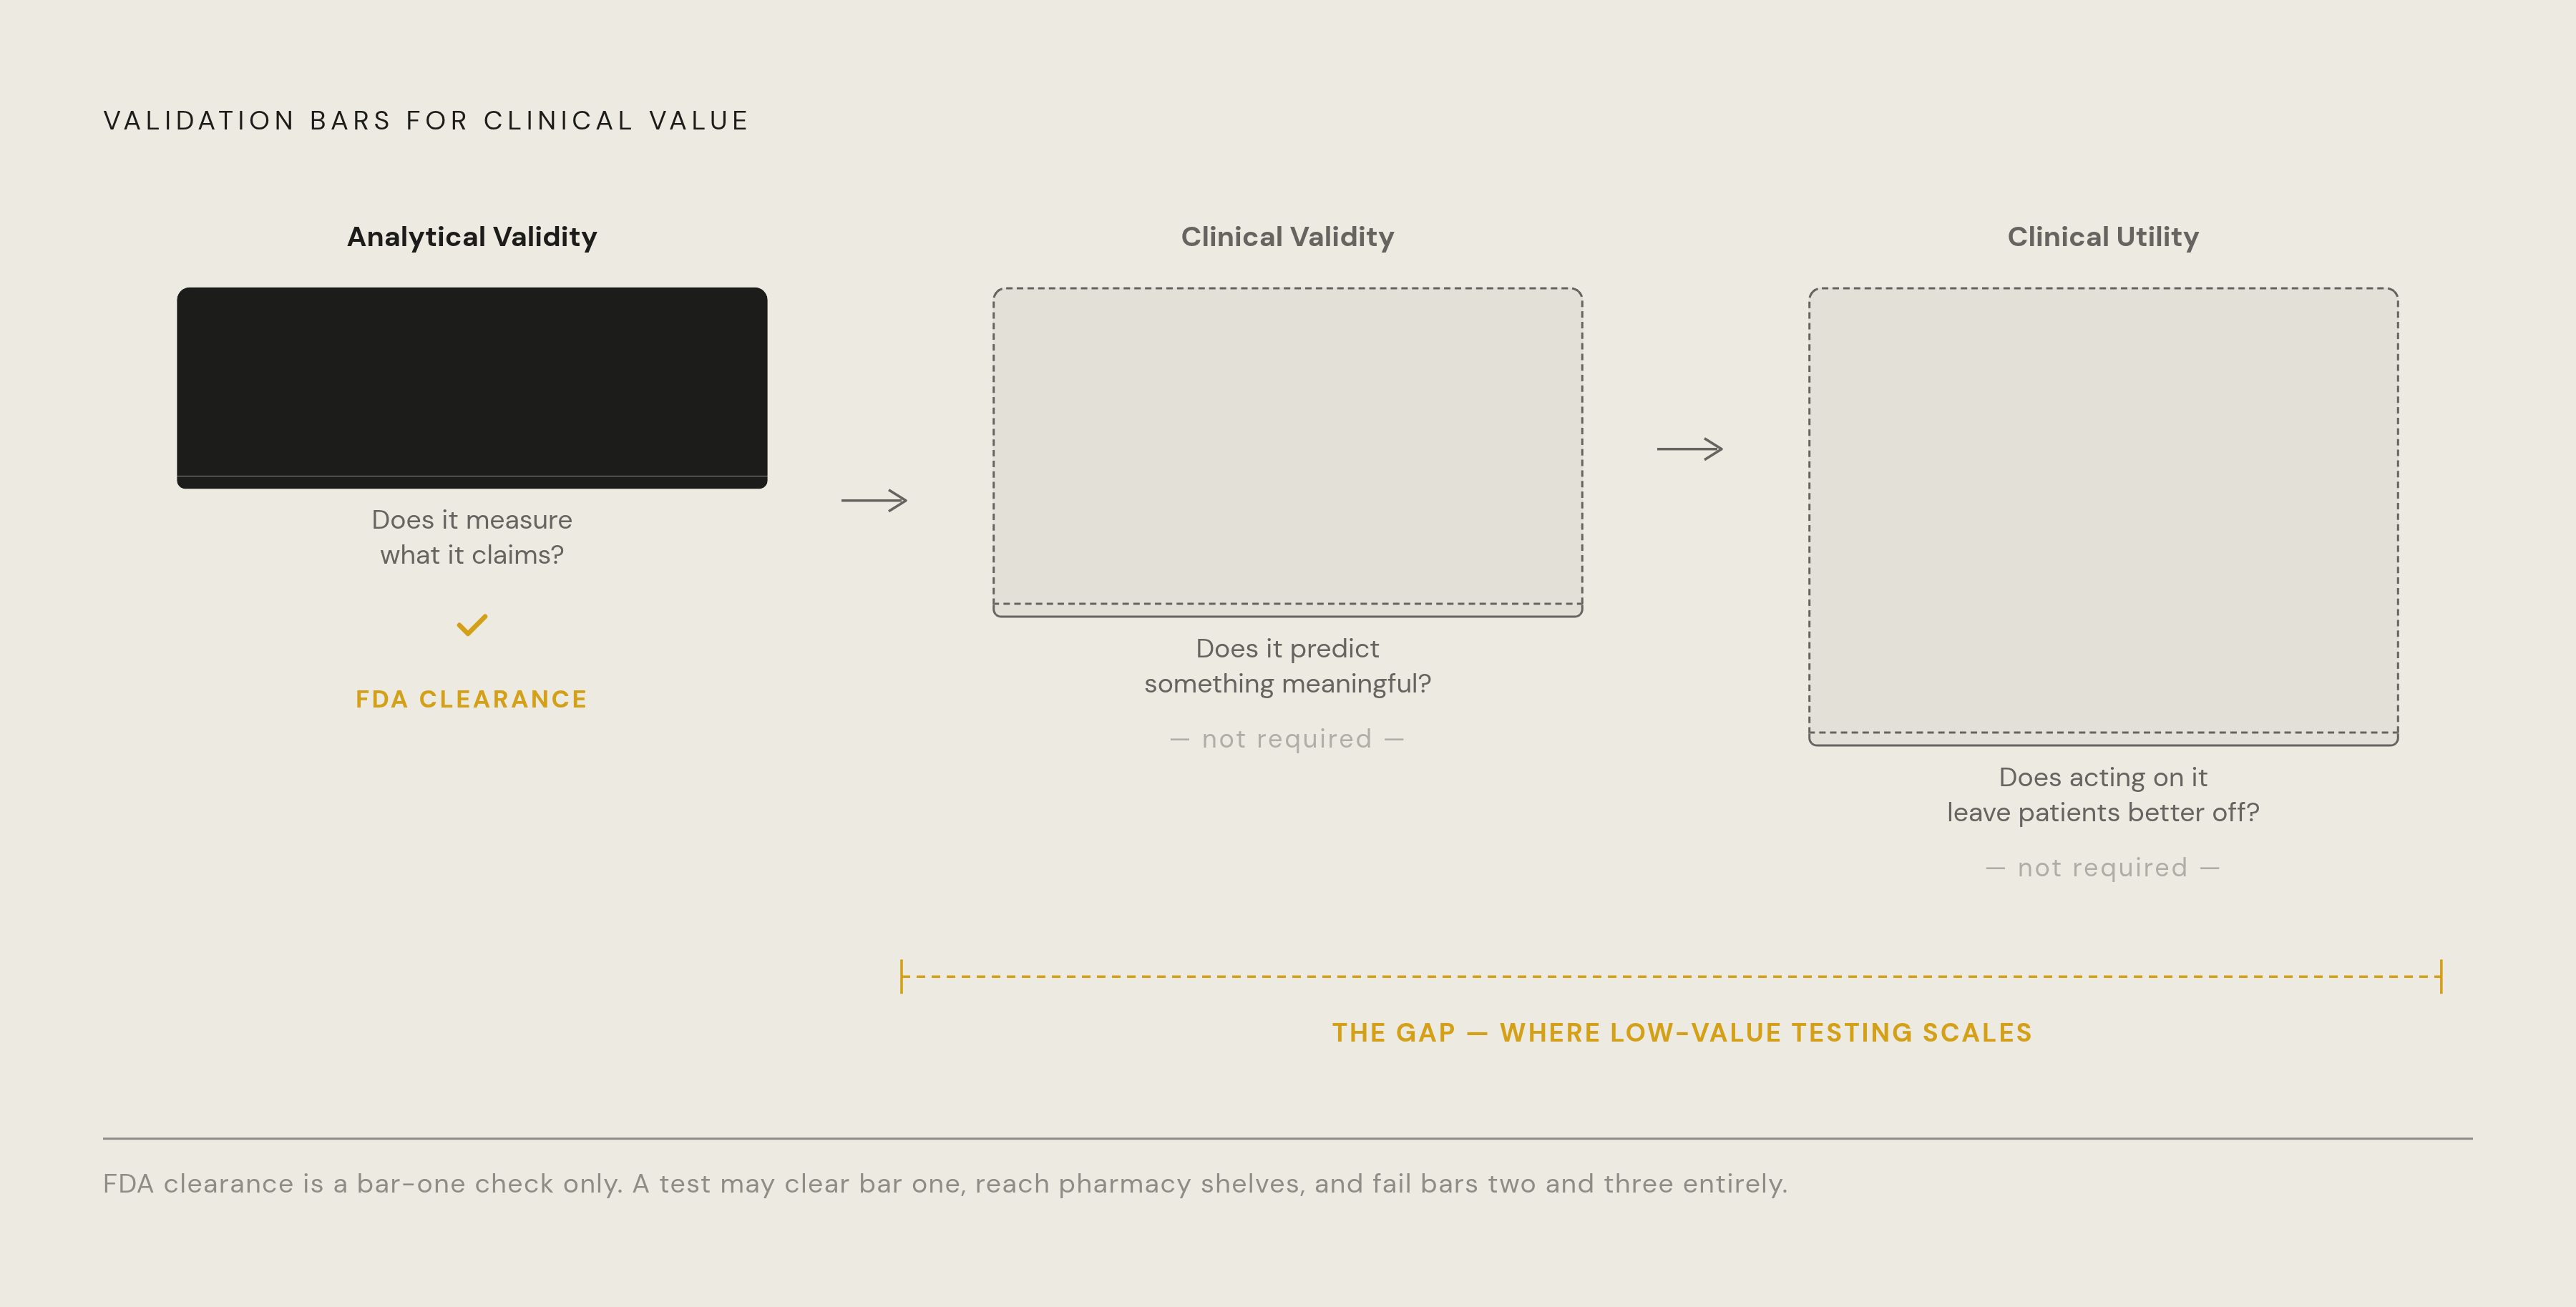
A test has to clear three separate bars to earn its place in care. Does the test measure what it claims to measure? That's what analytical validity asks. Clinical validity asks whether that measurement actually predicts something meaningful, a disease, a future event, a real biological state. Clinical utility asks the hardest question: does acting on the result change what happens to the patient, for the better? FDA clearance only checks the first bar. A test can be analytically sound, cleared, and sold with total confidence, and still fail to clear clinical utility, which is exactly the gap that lets low-value testing scale.
That gap is structural. FDA clearance doesn't require proof that a healthy person benefits from ordering the test, so the test can reach pharmacy shelves and direct-to-consumer catalogs without ever answering that question. Avalon's 2026 Lab Trend Report names the same tension from the clinical side: laboratory science can now offer far more than clinicians know how to use well, and that distance is growing every year, not shrinking.
So every test that follows in this piece gets measured against one question: will this result change what happens next, and will that change leave the patient better off? Tests that answer yes earn their place. Tests that only answer "yes, people buy it" do not.
How the DTC wellness panel market sells weak tests
The direct-to-consumer and self-pay testing market makes this evidentiary problem worst, because the way panels get priced and bundled makes it almost impossible to tell whether any single test inside the panel is actually warranted. If a 40-marker panel sells for one flat price, you never stop to ask whether marker number 27 has ever been shown to help anyone. It invites them to feel like they're getting a lot for their money.
A cross-sectional analysis of direct-to-consumer lab panel providers found exactly this pattern: panels routinely screen for multiple biomarkers despite limited or no evidence that testing healthy consumers, outside of a diagnostic reason, leads to meaningful health outcomes. The panel format itself is the problem. High-value tests and low-value tests get bundled together, the price makes the bundle look efficient, so the weak tests ride along because no one checks them one by one.
The damage rarely looks dramatic. It looks like a flagged number that leads to another test, then another, a chain of unnecessary follow-up that starts from a single low-value marker. It also looks like the opposite: a reassuring panel of normal results that delays a visit to an actual clinician when something real is going on, because the consumer now believes the wellness panel already covered it. Buyers in this market carry the least information about which tests are evidence-based and the most to lose if a result sends them down the wrong path.
Serum iron: the single number that routinely misleads
Serum iron measured on its own is one of the clearest cases of a popular test that actively misleads more often than it clarifies. Iron levels swing significantly across a single day, and they respond to recent meals, minor illness, and inflammation, so a person with real iron deficiency can post a normal serum iron, and a person with no deficiency at all can post an abnormal one.
The fix already exists, and it costs little more to run. Ferritin shows iron stores. Transferrin saturation shows iron actually in transit through the blood. C-reactive protein tells you whether an elevated ferritin reflects healthy stores or inflammation masking a deficiency underneath it. If you order those three together, serum iron stops adding any information.
The patterns these three markers reveal are the ones that matter clinically. Low ferritin paired with low transferrin saturation confirms true, absolute iron deficiency. High ferritin paired with elevated CRP points to a functional deficiency hiding inside an inflammatory state, a very different problem with a very different fix. Serum iron alone cannot tell these two situations apart. Anyone ordering it by itself, whether a clinician defaulting to habit or a consumer buying it as a standalone wellness check, is paying for a number that can point in the wrong direction as easily as the right one.
Total testosterone as a lone screen: why a single morning draw is diagnostically unreliable
Testosterone testing carries the same basic flaw as serum iron, and it occurs at much greater commercial scale, since testosterone is one of the most heavily marketed biomarkers in wellness testing today. Most testosterone circulating in the blood is bound to sex hormone-binding globulin, SHBG, so it isn't available to tissues. Total testosterone adds the bound and unbound fractions together, so the number it returns reflects SHBG levels nearly as much as it reflects actual androgen activity.
SHBG itself moves with obesity, liver disease, and estrogen exposure, conditions common in the exact population most likely to go looking for a testosterone test out of curiosity. That means total testosterone is most likely to mislead in precisely the people most likely to order it.
Timing adds another layer of noise. Testosterone follows a daily rhythm, and a draw taken outside the validated morning window can come back low for no reason other than the clock. Results can also differ meaningfully for the same person across different weeks or different labs, purely from assay variation, with no real change in hormone status behind it.
Free testosterone, or a calculated free androgen index (total testosterone divided by SHBG), answers the question most people actually came to ask: how much active androgen is available to the body right now? In men evaluated for suspected hypogonadism and in women evaluated for hyperandrogenism, evidence supports free testosterone as the more accurate marker. Total testosterone by itself doesn't clear that bar.
Total cholesterol as a cardiovascular risk screen
Cardiovascular testing is the highest-stakes category in this entire discussion, and total cholesterol, despite being decades old and run in nearly every annual physical, is a clear example of a ubiquitous test that functions poorly as a primary screen. The number folds protective cholesterol (HDL) and artery-clogging fractions into one figure. A high total cholesterol reading can come almost entirely from high HDL, which lowers risk rather than raising it, so the number alone can point a patient and a clinician in exactly the wrong direction.
ApoB solves this by counting particles instead of cholesterol content. It measures the actual number of atherogenic lipoprotein particles, LDL, VLDL, IDL, chylomicron remnants, and Lp(a), that are physically capable of lodging in an artery wall and starting a plaque. Plaque formation tracks with how many of these particles are circulating, regardless of how much cholesterol they happen to be carrying.
The data backing this up is specific. A Harvard Health study that followed 28,000 women found that LDL, CRP, and Lp(a) together predicted heart disease and stroke far more precisely than total cholesterol alone did. ApoB shows a stronger association with cardiovascular risk than LDL or total cholesterol show individually, and elevated ApoB also correlates with insulin resistance and broader metabolic dysfunction, giving it value beyond the heart alone.
If you want more than total cholesterol without ordering a full particle count, non-HDL cholesterol offers a simpler upgrade. It's a basic subtraction that captures every atherogenic fraction at once, and it holds up particularly well in patients with high triglycerides or metabolic syndrome, conditions where LDL calculations can run artificially low. The ApoB to ApoA-I ratio adds still another layer of risk prediction that total cholesterol can't give you on its own.
None of this means total cholesterol should vanish from every lab order. Advanced markers earn their place in patients who already carry elevated risk, where the extra precision changes management. Applying them indiscriminately across an undifferentiated population is a different decision, and the evidence supports the targeted use, not the blanket one.
IgG food sensitivity panels: a test category the evidence does not support
IgG food sensitivity panels fail in a different way than serum iron or total testosterone do. Those tests get outperformed by better alternatives. IgG panels fail at a more basic level: the premise behind the test has never been validated. If you measure IgG antibodies to food antigens, you haven't shown that those foods cause symptoms in the person you tested.
IgG antibodies to food are a normal, expected immune response to eating. Their presence tells you a person has eaten a given food at some point, not that their body reacts badly to it. That makes the test analytically valid, in that it measures real antibodies, and clinically uninterpretable as a sensitivity screen, because the measurement doesn't connect to the symptom it's being sold to explain.
The downstream harm is concrete. A broad IgG panel can flag dozens of foods as "reactive," and acting on that result by eliminating all of them brings real consequences: nutritional restriction, a psychological burden around eating that can follow a person for years, and a false sense of diagnosis that replaces the actual workup the symptoms deserved. The test's commercial popularity comes from this pattern: a panel that returns dozens of hits feels thorough, even though returning dozens of hits is what a test with no diagnostic meaning would be expected to do.
Validated alternatives already exist for the questions people are actually asking. IgE-mediated testing is the established approach for true food allergy. If you suspect a food intolerance, the established approach is a clinical elimination-and-challenge protocol done under supervision. IgG panels do not substitute for either one.
Multi-cancer early detection tests: genuine promise, premature routine use
Multi-cancer early detection tests deserve a more careful read than serum iron or IgG panels, because the technology behind them is genuinely promising, and the problem isn't fraud. Timing is the problem. Avalon's 2026 Lab Trend Report names MCED tests directly: they address a real clinical gap, screening for multiple cancers from a single blood draw, but the evidence base needed to support broad use today isn't there yet.
The gap is specific enough to spell out. A positive MCED signal doesn't always point to which organ the cancer might be in. When a patient tests signal-positive but turns out cancer-negative on further workup, providers have no standardized protocol to follow for what comes next. And the downstream consequences of detection, including the overdiagnosis of slow-growing cancers that would never have caused symptoms, haven't been tracked in long-term outcomes trials.
Alzheimer's blood biomarkers face a related version of the same problem. They offer a far less invasive option than a PET scan or a lumbar puncture, which is real progress. Avalon's 2026 report flags that these biomarkers are already being ordered in asymptomatic patients well outside the population they were validated for, ahead of where the supporting evidence actually extends.
For MCED tests, it isn't settled that earlier detection automatically improves outcomes. Conventional cancer screening programs have already documented the harm of overdiagnosing cancers that would never have become symptomatic, and MCED testing adds a new layer of that same risk rather than resolving it. None of this argues against the technology's future. It argues for separating "promising" from "ready for routine use in healthy adults," because right now, those are two different claims.
Monitoring tests for established conditions drifting into low-value territory
Low-value testing isn't confined to the DTC wellness market. It shows up inside routine clinical monitoring of conditions patients already have, managed by their own clinicians, with no wellness panel in sight. Advisory Panel guidance on minimum retesting intervals estimated that around 22% of blood tests performed in Canada were likely unnecessary, and that figure is large enough to suggest the pattern runs deep inside standard care.
A UK audit of general practitioners' monitoring habits found that GPs really disagreed over when to order liver function tests and full blood counts, routinely, sometimes, or never, for patients with specific long-term conditions. That disagreement didn't come from sloppy judgment. It came from a genuine absence of clear outcomes evidence that could tell clinicians how often these tests should actually run.
Three forces drive the over-ordering, and none of them involve bad intent: guidelines built on expert opinion rather than outcomes data, a clinician's fear of missing something important, and patients who expect a certain test to be run as a matter of course. In the same audit, only about half of GPs surveyed said they felt confident acting on an abnormal result once they had one, a reminder that ordering a test and knowing what to do with its result are two separate skills. The lesson for any patient trying to test proactively: even a test with a legitimate, well-established clinical use can turn into a low-value habit the moment it's ordered without a specific question attached to it.
What separates a well-chosen test from a popular one
A well-chosen test starts from a question. Before a number gets drawn, the question is whether, if this result comes back abnormal, what changes, and does that change actually help. IgG panels fail it because the premise behind the test was never sound. MCED tests haven't failed it so much as arrived before the evidence needed to answer it.
None of this argues for testing less out of caution alone. It argues for testing on purpose. ApoB, non-HDL cholesterol, free testosterone, ferritin alongside transferrin saturation and CRP: each of these exists because it answers a sharper question than the test it replaced. That's the real standard a test should meet, not how many panels it appears in, not how confidently it's marketed, but whether acting on its result leaves the person who ordered it better off than they were before.